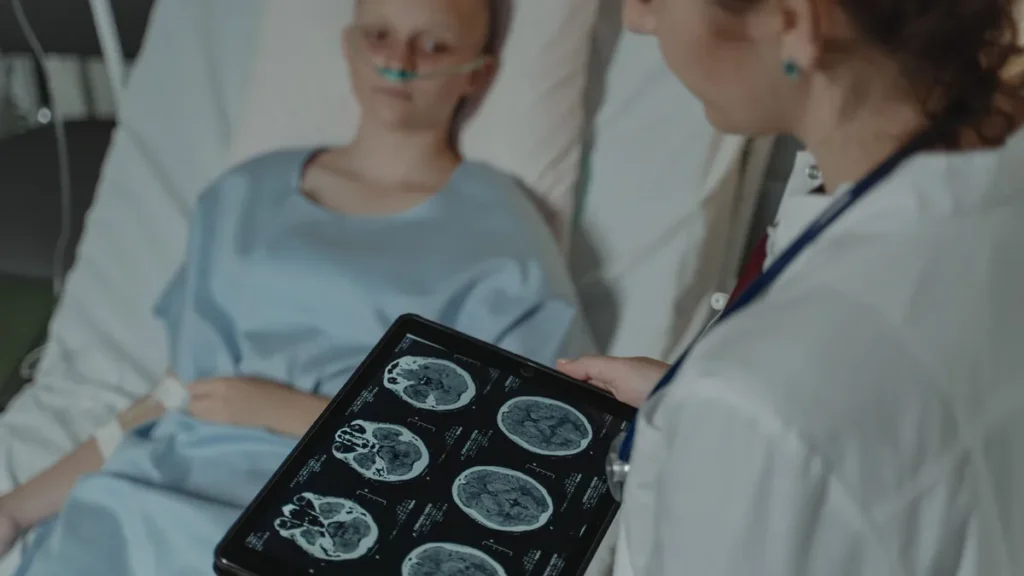
Yes, you can have a concussion with a normal CT scan. CT finds bleeding and broken bones. Concussion damage happens in tiny nerve fibers called axons. Blood biomarkers such as GFAP and UCH-L1 are proteins that leak from injured brain cells. They carry the evidence the scan cannot show.
You were told the scan looked fine. You went home with a normal CT and a few calming words. Weeks later the fog has not lifted. Somewhere in the back of your mind, you wonder if you are imagining it.
You are not. A standard CT scan is very good at one job: finding blood and fractures that need a brain surgeon tonight. It was never built to find the tiny injury that causes lasting brain fog. A clear CT rules out an emergency. It does not rule out a concussion.

Watch on YouTube: Concussion: The Invisible Injury
Why doesn’t a CT scan show a concussion?
A concussion is not mainly a structural problem you can take a picture of. The damage happens at the level of single cells. Axons are the long wires that carry signals between parts of the brain. Fast speeding up and slowing down stretches and tears them. The injury is real, and it is measured in microns. A CT scanner sees millimeters.
This is why the question “is anything showing up on the picture?” is the wrong question. The better question is whether your brain has leaked the chemical evidence of injury into your blood.
Is there a blood test for concussion?
When brain cells are damaged, what is inside them spills into the blood. Two of these proteins can now be measured in routine care:
- GFAP (glial fibrillary acidic protein) comes from astrocytes. These are the support cells that hold up and feed nerve cells (neurons).
- UCH-L1 (ubiquitin C-terminal hydrolase L1) comes from the neurons themselves.
They come from different kinds of cells, so the pair tells you different things. Broadly, GFAP points to injury in support cells and UCH-L1 to injury in neurons. Both rise within hours of trauma. That makes them useful early, while a patient is still deciding whether this is serious.
This part is established, not experimental. A combined GFAP/UCH-L1 blood test has been cleared by the FDA to help doctors decide which head-injured patients really need a CT scan. Used well, it can spare people a high-radiation scan that would never have helped them.
Which blood markers matter when concussion symptoms last?
If symptoms last past the acute window, two more proteins matter:
- Neurofilament light chain (NfL) is a building-block protein from the axon itself. It can stay high for months. So it is less a snapshot and more a running record of ongoing axonal degeneration (axons breaking down).
- Tau is associated with repeated hits to the head. It is studied as a sign of longer-term risk to thinking and memory.
Classify these honestly: NfL and tau are still research markers in this setting. They are strong research tools, and clinics use them more and more. But they are not the settled, cleared test that the GFAP/UCH-L1 pair has become for the acute CT decision. Anyone who calls a tau result a diagnosis of long-term brain disease is overselling what the test can support today.
The same caution goes for inflammatory cytokines and microRNA signatures. We track them as part of a bigger picture of how your nervous system is responding. They are not verdicts on their own.
What other tests can find a concussion when the CT is normal?
Two other lines of evidence matter when standard imaging shows nothing.
Advanced MRI. Diffusion tensor imaging (DTI) checks the health of the brain’s white-matter wiring. It can show damage that standard scans miss. It is not what a standard machine gives you by default.
Eye movement. Eye control runs through the brainstem, so the eyes are a direct window into it. Eye tracking can catch small errors in quick eye jumps (saccades) and smooth pursuit. These errors are far too small to notice in yourself. These digital biomarkers measure performance, not mood. They do not depend on how you feel the morning of the test, or on whether anyone believes you.
What most clinics will not tell you
Biomarkers are not a magic bullet. Be wary of anyone who sells them that way.
Today’s biomarkers have modest effect sizes. Values from injured people can overlap with values from healthy ones. That overlap is real. It is the honest limit of the whole field. Despite FDA clearances, many insurers still refuse to cover these tests — a coverage decision, not a scientific one, but one that shapes what gets ordered.
This is exactly why no single number should decide anything. One data point is a guess to be tested. A pattern across blood, imaging, eye performance and your real clinical history is evidence.
Frequently asked questions
Can I have a concussion if my CT scan was normal?
Yes. A CT scan is built to find bleeding and skull fractures that need emergency care. Concussion is mostly a tiny, functional injury. So a normal CT is expected in most concussions. It does not mean you were not hurt.
What do GFAP and UCH-L1 actually measure?
They are proteins that spill into the blood when brain cells are damaged. GFAP comes from astrocytes, the brain’s support cells. UCH-L1 comes from neurons. Both rise within hours of injury. A combined test has FDA clearance to help decide whether a CT scan is needed.
Are NfL and tau tests diagnostic for long-term brain damage?
No. Neurofilament light and tau are useful, but treat them as research markers here. NfL can stay high for months and reflects ongoing axonal degeneration. Tau is associated with repeated injury and is studied as a risk signal. Neither one makes a diagnosis on its own.
Why would my insurance not cover a test the FDA cleared?
FDA clearance and insurance coverage are separate decisions. Many payers still decline to cover concussion biomarker testing despite clearance. That is a reimbursement policy judgment, and it is worth asking about cost before testing.
How do doctors check for concussion?
When the CT is clear, the evidence has to come from several places at once. Blood tests for GFAP and UCH-L1 look for proteins that leak from injured brain cells. Advanced MRI with diffusion tensor imaging can show white-matter damage a standard scan misses. Eye tracking measures small errors in eye control. No single number decides it. The pattern across these tests and your clinical history does.
What does a positive GFAP test mean?
GFAP is a protein that comes from astrocytes, the support cells that hold up and feed neurons. When those cells are hurt, GFAP enters the blood. It rises within hours of trauma. A high level points to injury in those support cells. It is not a verdict on its own. Values from injured and healthy people can overlap. So one result is a lead to check against the rest of the evidence.
Where is Injury Experts located?
Injury Experts is at 4477 Woodson Rd, Suite 202, St. Louis, MO 63134, next to Lambert International Airport, serving the St. Louis region across Missouri and Illinois. Call (314) 887-5866 or text (314) 886-5902.
Get your injury validated by science, not by an adjuster's spreadsheet
We turn subjective pain into objective, court-ready evidence — biomarkers, biomechanics and diagnostic blocks. Bring us your case before the insurer defines it for you.
Or call or text us.
Key takeaways
- A normal CT rules out a surgical emergency, not a concussion.
- GFAP and UCH-L1 are established, FDA-cleared aids to the CT decision.
- NfL, tau, cytokines and microRNA signatures are useful research markers, not diagnoses.
- Eye tracking and DTI measure performance and structure that standard scans and self-report both miss.
- Biomarker values overlap between injured and healthy people, so no single result should decide your care or your case.
Sources
- Papa L, Brophy GM, Welch RD, et al. Time course and diagnostic accuracy of glial and neuronal blood biomarkers GFAP and UCH-L1 in a large cohort of trauma patients with and without mild traumatic brain injury. JAMA Neurol. 2016;73(5):551–560. doi:10.1001/jamaneurol.2016.0039 (PMID 27018834)
- Bazarian JJ, Biberthaler P, Welch RD, et al. Serum GFAP and UCH-L1 for prediction of absence of intracranial injuries on head CT (ALERT-TBI): a multicentre observational study. Lancet Neurol. 2018;17(9):782–789. doi:10.1016/S1474-4422(18)30231-X (PMID 30054151)
This article is for general education and is not medical advice. It does not create a physician–patient relationship. Do not start, stop, or change any medication or treatment without consulting your physician. If you have had a head injury and develop worsening headache, repeated vomiting, seizures, weakness, or increasing confusion, seek emergency care immediately.
Medically reviewed by Dr. Gurpreet Singh Padda, MD, MBA, MHP — Board Certified in Anesthesiology, Pain Medicine, Interventional Pain Management, Addiction Medicine, and Obesity Medicine.